

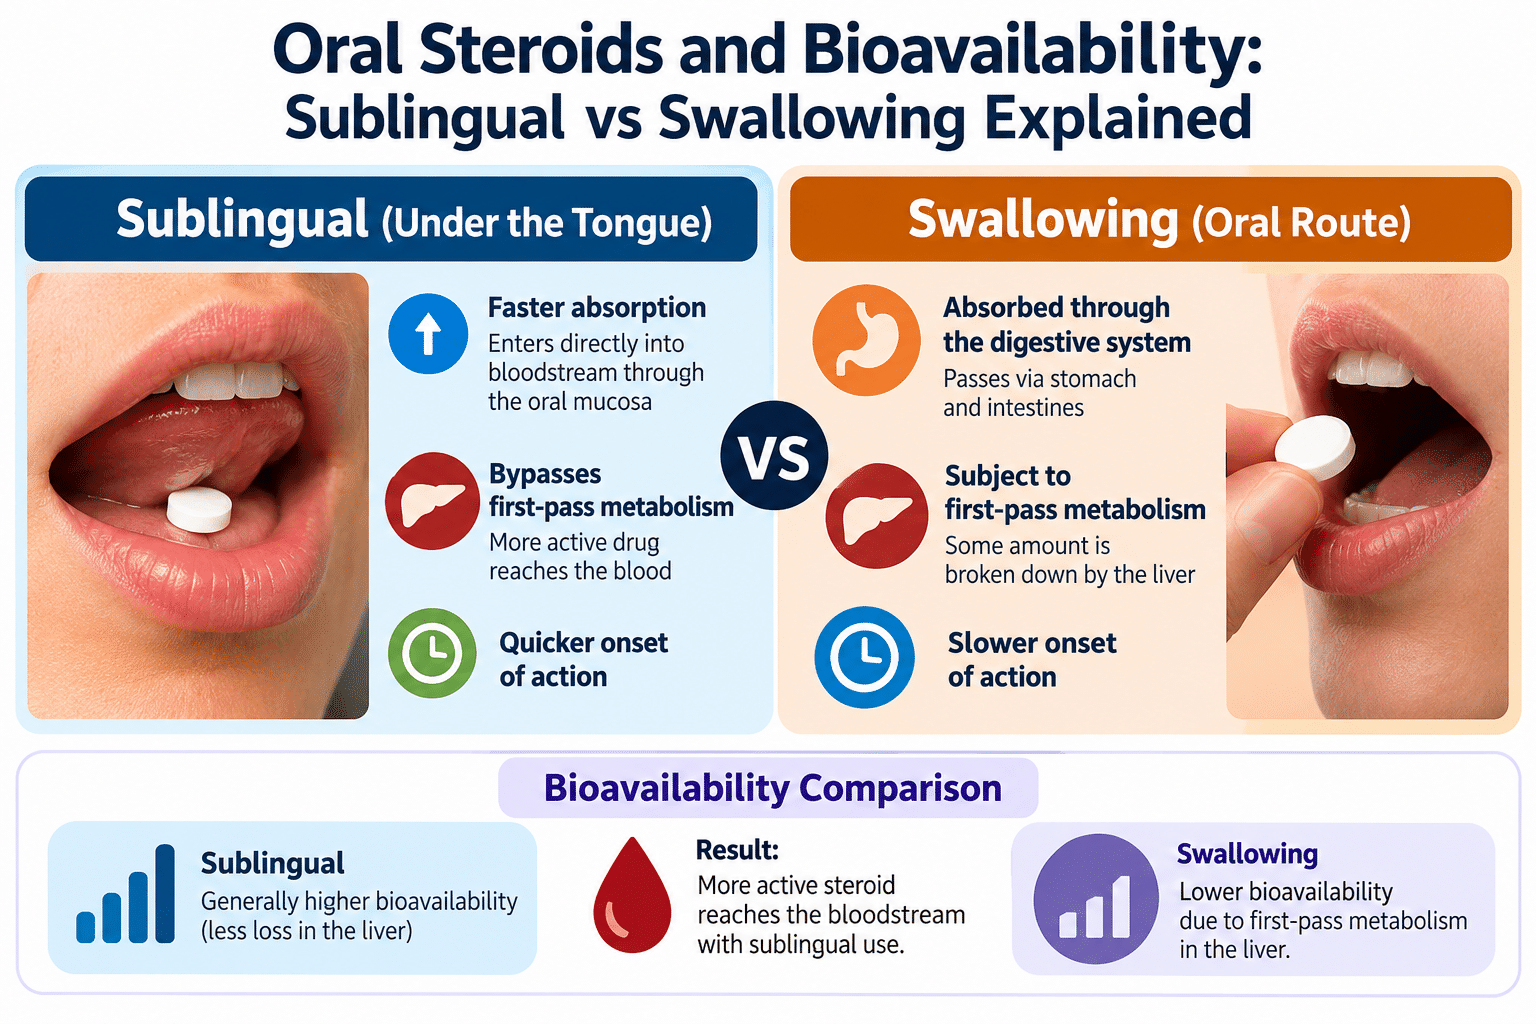
A swallowed tablet can lose a substantial share of its active compound before it ever reaches the bloodstream, while the same dose placed under the tongue can bypass that loss almost entirely. For anyone researching oral steroids, that single difference explains why sublingual dosing has become a serious talking point in UK fitness and performance circles, not just a marketing gimmick.
Quick Answer
Sublingual delivery allows a compound to absorb directly through the mucous membranes under the tongue, entering the bloodstream without first passing through the liver. Swallowing sends the same compound through the digestive tract and liver first, where hepatic enzymes break down a large portion before it reaches general circulation. For oral steroids specifically, this matters because the liver is the organ most responsible for both low oral bioavailability and oral-related liver strain.
Key Takeaways
- Sublingual absorption bypasses first-pass liver metabolism; swallowing does not.
- Pharmacokinetic comparisons have recorded sublingual bioavailability roughly 2 to 3 times higher than oral swallowing for suitable compounds.
- Not every oral steroid is formulated or chemically suited to sublingual use.
- 17-alpha-alkylated oral steroids, such as Anavar, are already engineered to survive the liver, which is different from sublingual avoidance of it.
- Sublingual dosing can reduce, but does not eliminate, liver exposure or hepatotoxicity risk.
- Holding time under the tongue (typically 30 to 90 seconds) directly affects how much is absorbed versus swallowed by accident.
- In the UK, anabolic steroids are Class C controlled substances; possession for personal use is legal, but supply and import carry criminal penalties.
- Faster absorption does not automatically mean better clinical or performance outcomes.
What Does Sublingual Mean, and How Does It Work
Sublingual means “under the tongue.” A tablet, drop, or film is held in the mouth where it dissolves in a small volume of saliva and absorbs directly through the thin mucosal tissue beneath the tongue.
That tissue sits close to a dense network of small blood vessels. Once a compound crosses the mucosal membrane, it enters those vessels and travels straight into systemic circulation. It does not pass through the stomach, intestines, or liver before reaching the rest of the body. This route works best for lipophilic (fat-soluble) molecules, which is exactly what most steroid hormones are.
Sublingual vs Swallowing: What Is the Real Bioavailability Difference
Sublingual absorption can deliver a meaningfully higher fraction of a dose into the bloodstream compared with swallowing the same dose. The gap exists because swallowed compounds must survive stomach acid, gut enzymes, and the liver before any of the drug reaches general circulation.
Research comparing equivalent doses of the same compound by each route has recorded oral bioavailability around 25 percent (give or take roughly 8 percentage points) versus about 63 percent (give or take roughly 22 percentage points) when taken sublingually, a roughly 2.5-fold increase. Other formulation reviews describe sublingual routes delivering more than double the bioavailability of matched swallowed doses for several active ingredients. The exact multiplier varies by compound, formulation, and individual physiology, but the direction is consistent: sublingual routes generally outperform swallowing for molecules vulnerable to liver breakdown.
How the Liver Processes Oral Steroids (First-Pass Metabolism Explained)
The liver processes oral steroids through what pharmacologists call first-pass metabolism, converting and deactivating a large share of the compound before it ever reaches the bloodstream. This is the central reason unmodified oral steroids, including unmodified testosterone, are considered to have very low oral bioavailability.
Here is the route a swallowed tablet actually takes:
- The tablet dissolves in the stomach and small intestine.
- Absorbed molecules enter the portal vein, which carries blood directly to the liver.
- Liver enzymes metabolize a significant portion of the compound, often inactivating much of it before it reaches systemic circulation.
- Only the surviving fraction reaches the rest of the body to produce an effect.
This is why many natural steroid hormones are effectively useless when swallowed in unmodified form, and why pharmaceutical science has turned to either chemical alteration or transmucosal delivery as workarounds.
Does Sublingual Delivery Actually Bypass the Liver
Yes, in part. Sublingual absorption lets the fraction of compound that crosses the mucosal membrane enter the bloodstream directly, skipping the initial pass through the portal vein and liver that swallowing requires.
That said, “bypass” does not mean “avoid entirely.” Any portion of a sublingual dose that gets swallowed, along with saliva, still travels the normal digestive route and faces first-pass metabolism. And once absorbed compound circulates through the body, it eventually passes through the liver during normal blood circulation anyway, just later and without the immediate, concentrated hit that swallowing produces. Sublingual dosing reduces initial hepatic load; it does not remove the liver from the picture altogether.
Which Oral Steroids Work Better Sublingual vs Swallowed, and What Comes in Sublingual Form
Steroid hormones that are highly lipophilic and heavily degraded by first-pass metabolism tend to show the biggest sublingual advantage. Testosterone and estradiol are the most documented examples, which is why sublingual and buccal testosterone products already have an established place in hormone replacement therapy.
- Sublingual testosterone drops or tablets: used clinically; studies show peak blood levels around 10 to 20 minutes after dosing, with levels returning to baseline within roughly 2 to 2.5 hours.
- Buccal testosterone tablets: adhere to the gum or cheek for sustained release rather than a quick spike.
- 17-alpha-alkylated orals (for example, Anavar/oxandrolone, stanozolol): formulated specifically to survive swallowing and the liver, so sublingual use offers a smaller relative advantage since the compound is already liver-resistant.
Choose sublingual if the compound in question is unmodified or known to suffer heavy first-pass loss. Choose standard swallowed tablets if the compound has already been chemically altered to withstand the liver, since the sublingual benefit shrinks considerably in that case.
Can You Put Any Oral Steroid Under the Tongue
No. Physically holding a tablet under the tongue does not guarantee meaningful sublingual absorption, because many tablets are formulated for gut dissolution, not mucosal uptake.
A tablet designed for swallowing often has a coating or binder structure meant to survive stomach acid and release slowly in the intestine. Placing it under the tongue does not reliably reformulate it into a fast-dissolving sublingual product. True sublingual products (drops, films, specially formulated micro-tablets) are engineered with rapid-disintegration excipients so the active compound releases within the mouth, not the gut. Using a standard swallowed tablet sublingually is an edge case with unpredictable, usually reduced, absorption compared with a purpose-built sublingual formulation.
Anavar and the Oral vs Injectable Bioavailability Question
Anavar (oxandrolone) illustrates why oral steroid bioavailability is a separate issue from injectable bioavailability, not simply a weaker version of it. Anavar is 17-alpha-alkylated, a chemical modification that protects the molecule from being broken down on its first pass through the liver, which is why it works at all when swallowed.
Injectable steroids skip the digestive tract and liver first-pass entirely by entering muscle tissue or the bloodstream directly, which is why most injectable compounds do not need 17-alpha-alkylation and generally carry a lower liver burden per dose. Anavar’s oral route, by contrast, still sends the compound through hepatic circulation; the alkylation reduces breakdown but concentrates metabolic stress on the liver over time. This is the core trade-off UK users researching oral steroids need to understand: oral convenience versus a liver-mediated route, compared with injectable directness versus needle-based administration and its own risks.
Why Choose Sublingual Over Regular Pills (and Is It Just Marketing)
People choose sublingual delivery for faster onset, higher absorbed fraction, and reduced initial liver exposure, and the underlying pharmacology genuinely supports these claims for suitable compounds. It is not pure marketing, but the benefit is compound-specific, not universal.
The advantage is real and measurable for molecules like unmodified testosterone or estradiol, where oral bioavailability is otherwise very low. It is far less relevant for compounds already designed to survive swallowing, such as alkylated oral steroids, where the liver-resistance is built into the molecule rather than achieved through delivery route. Marketing language that implies sublingual use makes any steroid “liver-safe” or universally superior overstates the evidence.
Same Results Sublingually vs Swallowed? Side Effects and Safety Compared
Sublingual dosing can produce comparable or even stronger hormonal effects at a lower dose than swallowing, because more of the compound actually reaches circulation, but this does not automatically mean sublingual use is safer overall.
- Liver strain: generally lower initially with sublingual use, since first-pass exposure is reduced, but systemic liver exposure still occurs once the compound circulates.
- Peak intensity: sublingual testosterone can produce a sharp, rapid spike in blood levels, which may increase side effects tied to high peak concentrations (such as mood changes or cardiovascular strain) even if total liver load is lower.
- Dose accuracy: sublingual liquids and drops are harder to dose precisely than manufactured tablets, increasing the risk of under- or over-dosing.
- Clinical outcomes are not guaranteed: pharmacodynamic research on sublingual testosterone in premenopausal women found no significant change in subjective or physiological measures despite improved absorption, showing that better bioavailability does not always translate into better results.
Edge case: someone with pre-existing liver concerns might reasonably prefer a sublingual route for a compound prone to first-pass damage, but should still expect ongoing medical monitoring, not elimination of risk.
How Long to Hold a Sublingual Dose, and What Happens If You Swallow It
Most sublingual steroid products are designed to be held under the tongue for roughly 30 to 90 seconds, with some clinical protocols using 30 to 60 seconds once daily, allowing the dissolved compound time to absorb through the mucosa before any saliva is swallowed.
If the dose is swallowed too early, a large portion effectively converts into a standard oral dose, subject to full first-pass liver metabolism, undermining the reason for choosing the sublingual route in the first place. Common mistake: talking, eating, or drinking immediately after dosing, which washes the compound away from the mucosal membrane before absorption completes. For consistent results, the dose should sit undisturbed for the full recommended hold time, then whatever remains can be swallowed normally.
Comparison at a Glance
Factor Swallowing (standard oral) Sublingual Liver first-pass exposure Full, immediate Reduced, not eliminated Typical bioavailability Lower (varies by compound) Higher for suitable compounds Onset speed Slower (digestion required) Faster (minutes, not hours) Dose precision Generally more consistent Can be less precise (drops/liquids) Suited compounds Alkylated orals, acid-stable drugs Lipophilic steroids, fast-acting needs UK legal status (personal possession) Class C, possession legal Class C, same legal status FAQ
What does sublingual mean in simple terms?
Sublingual means placing a substance under the tongue so it absorbs through the mouth’s mucous membrane directly into the bloodstream, rather than being swallowed and digested.
Do sublingual supplements absorb faster than swallowing pills?
Yes, generally. Sublingual absorption can begin within minutes because the compound enters blood vessels directly, while swallowed pills must first pass through digestion and the liver.
Does sublingual dosing bypass the liver completely?
No. It bypasses the initial first-pass metabolism, but any swallowed portion of the dose, plus everything absorbed, eventually circulates through the liver during normal blood flow.
Can you put any oral steroid tablet under the tongue for better absorption?
Not reliably. Standard swallowed tablets are formulated for gut dissolution, not mucosal absorption, so sublingual use of them often gives inconsistent or reduced results.
Is Anavar sublingual or swallowed?
Anavar (oxandrolone) is a 17-alpha-alkylated oral steroid, formulated to be swallowed and survive the liver through its chemical structure, not through sublingual delivery.
Are sublingual steroids safer than swallowed oral tablets?
They can reduce initial liver exposure, but safety depends on total dose, peak blood concentration, and individual health factors, so “safer” is not a guaranteed outcome.
How long should a sublingual steroid dose be held in the mouth?
Most protocols call for roughly 30 to 90 seconds, allowing the mucosal tissue time to absorb the dissolved compound before swallowing any remainder.
What happens if you swallow a sublingual dose by accident?
It largely converts into a standard oral dose, subjecting a much larger share of the compound to first-pass liver metabolism and reducing the intended bioavailability benefit.
Is the UK sublingual steroid trend just marketing hype?
Partly evidence-based. The pharmacology supports faster absorption and reduced first-pass loss for suitable compounds, but claims of universal safety or superiority over all oral steroids are overstated.
Conclusion
Bioavailability differences between sublingual and swallowed delivery come down to one organ: the liver. Swallowing sends compounds through hepatic first-pass metabolism before they can act, while sublingual delivery lets a larger fraction reach circulation directly. For oral steroids such as unmodified testosterone, that difference is large and clinically documented. For chemically altered compounds such as Anavar, the liver-resistance is already built in, so the sublingual advantage is smaller and the liver is still involved over time regardless of route.
Anyone weighing this decision should start by identifying whether the specific compound is lipophilic and prone to heavy first-pass breakdown, or already structurally modified to survive swallowing. From there, match the delivery method to the compound’s actual pharmacology rather than assuming sublingual use is automatically faster, stronger, or safer. UK readers should also remember that anabolic steroids remain Class C controlled substances; understanding bioavailability is a matter of pharmacological literacy, not an endorsement of unsupervised or unlawful use, and any decision involving hormone compounds should involve a qualified medical professional.
Source
https://steroids-uk.com/
https://steroids-uk.com/product-category/oral/
